Emotional AI systems that infer mood, stress, or affect from language, voice, facial cues, or behavior have moved from research labs into apps, clinics, and workplace tools. In 2026, these systems are more capable and more visible than ever: they screen for depression, offer low‑intensity cognitive behavioral therapy (CBT) exercises, and provide clinicians with session summaries. At the same time, evidence about long‑term effectiveness, fairness, and safety remains mixed.
This article explains how emotional AI works, summarizes the best available evidence, highlights practical use cases and risks, and gives concrete guidance for clinicians, product teams, and everyday users who want to adopt these tools responsibly. The goal is pragmatic: show what emotional AI can do today, where it falls short, and how to deploy it without causing harm.
How emotional AI works
Emotional AI is not a single technology but a family of methods that map observable signals to affective states. The most common approaches include:
- Natural language processing (NLP): Models analyze text—chat messages, journal entries, or therapy transcripts—to detect sentiment, negative thinking patterns, or linguistic markers associated with depression and anxiety.
- Speech and voice analysis: Acoustic features such as pitch, tempo, pauses, and spectral qualities can correlate with mood and cognitive load. Voice models extract these features and map them to risk scores.
- Computer vision: Facial expression analysis and micro‑expression detection use visual cues to infer affective states, though performance varies across lighting, camera quality, and cultural display rules.
- Behavioral analytics: Interaction patterns—frequency of app use, sleep and activity data from wearables, typing speed—can provide indirect signals of wellbeing.
Most practical systems combine multiple channels (multimodal models) to improve sensitivity. Models are trained on labeled datasets—clinical interviews, annotated conversations, or crowdsourced labels—and validated against clinical scales or diagnostic interviews. Performance depends heavily on the quality and representativeness of training data, the rigor of validation, and the deployment context.
What the evidence shows
The research landscape in 2026 is clearer than it was five years earlier, but still nuanced.
- Conversational agents and chatbots: Randomized trials and meta‑analyses show small‑to‑moderate short‑term reductions in depressive symptoms for some chatbot interventions, particularly those delivering structured CBT exercises. Effects are often comparable to low‑intensity human‑led interventions in the short term, but long‑term outcomes and relapse prevention data are limited.
- Screening tools: Automated screening using text or voice features can achieve high sensitivity in controlled settings for specific tasks (e.g., detecting major depressive disorder), but external validation across diverse populations is inconsistent. False positives and negatives remain a concern.
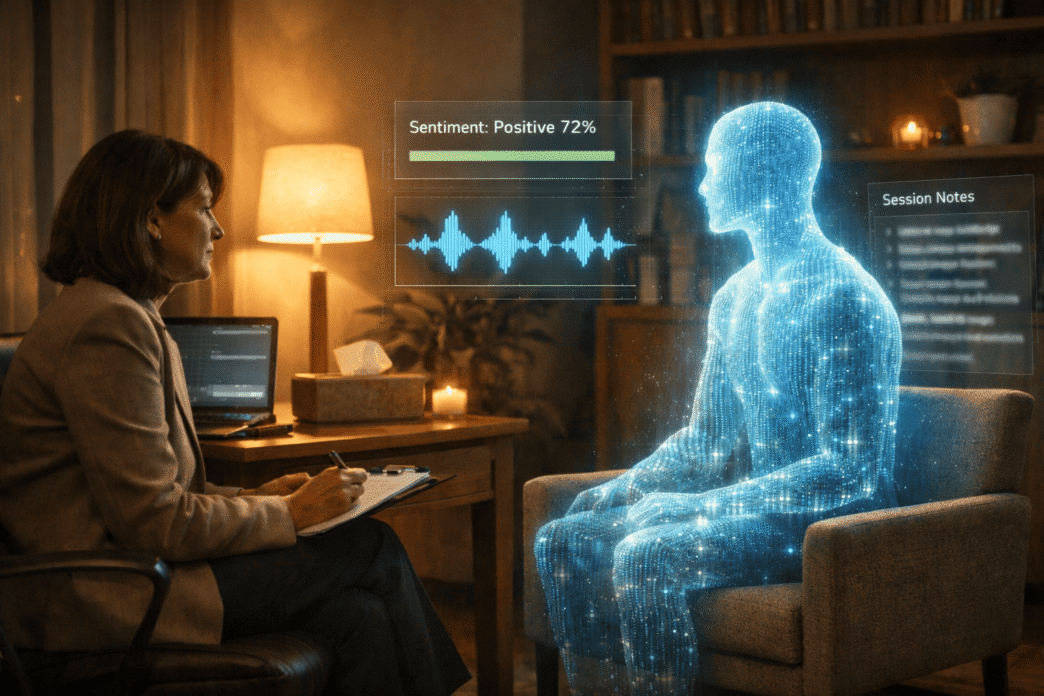
- Augmented clinical workflows: Tools that summarize session sentiment, flag risk trends, or provide clinician dashboards can improve efficiency and help clinicians spot changes between visits. Evidence suggests these tools are useful as adjuncts but require careful integration to avoid alert fatigue.
- Equity and bias: Many studies report performance gaps across demographic groups. Models trained on data from high‑income countries or specific cultural contexts often underperform for underrepresented populations. This is a persistent problem that requires targeted data collection and fairness testing.
Leading reviews from major journals and health organizations emphasize cautious optimism: emotional AI can expand access and provide scalable screening, but robust clinical trials, transparent reporting, and ethical safeguards are essential before broad clinical adoption.
Practical use cases and examples
1. Triage and early detection
Primary care clinics use brief automated questionnaires and voice analysis to flag patients who need follow‑up. For example, a clinic integrates a voice‑based screener into intake calls; callers with sustained low pitch and slowed speech are routed for a same‑day behavioral health consult. This reduces missed cases and shortens wait times.
2. Low‑intensity support
Apps deliver CBT exercises, mood tracking, and guided breathing. A university deploys a chatbot that offers evidence‑based coping strategies and crisis resources; students use it for immediate support outside counseling hours. The chatbot escalates to human counselors when risk thresholds are crossed.
3. Clinician augmentation
Therapists receive session summaries that highlight sentiment trends, recurring negative themes, and patient‑reported outcomes. One clinic found that clinicians used these summaries to tailor homework assignments and to notice subtle deteriorations between sessions.
4. Workplace wellbeing
Employers offer opt‑in emotional AI tools that provide anonymous aggregated insights about team stress levels. When a team shows rising stress signals, leadership invests in workload adjustments and targeted support. Privacy and consent are central to these deployments.
Risks, limitations, and ethical concerns
Emotional AI brings real benefits but also real risks:
- False positives and negatives: Misclassification can cause unnecessary alarm or missed crises. In high‑stakes settings, errors have serious consequences.
- Privacy and data security: Emotional data is highly sensitive. Poorly secured systems or vague consent practices can expose intimate details about mental health.
- Cultural bias: Affect expression varies across cultures. Models trained on one population may misinterpret signals from another, producing biased outcomes.
- Overreliance and deskilling: Clinicians or users may overtrust automated outputs, reducing critical judgment. Tools should support—not replace—human expertise.
- Transparency and explainability: Black‑box models that provide risk scores without clear rationale undermine trust and make it hard to contest decisions.
- Commercialization and monetization: Some consumer apps prioritize engagement over clinical benefit, using persuasive design that may increase dependency rather than resilience.
Addressing these risks requires technical, organizational, and regulatory measures.
Practical guidance for clinicians and organizations
If you are evaluating or deploying emotional AI, follow these practical steps:
1. Start with a clear clinical question
Define the specific problem the tool will address: screening, triage, augmentation, or self‑help. Avoid one‑size‑fits‑all solutions.
2. Demand external validation
Require peer‑reviewed evidence or independent evaluations that report sensitivity, specificity, calibration, and subgroup performance. Look for trials with clinically meaningful endpoints and follow‑up.
3. Integrate human oversight
Design workflows where clinicians review flagged cases and where users can easily connect to human support. For high‑risk flags, require immediate human follow‑up.
4. Protect privacy and consent
Use strong encryption, minimize data retention, and obtain explicit informed consent that explains what data are collected, how they are used, and who can access them.
5. Monitor fairness and performance
Continuously monitor model performance across demographic groups and contexts. Use disaggregated metrics and involve diverse stakeholders in evaluation.
6. Provide transparency and explainability
Offer clear explanations of what the model measures, its limitations, and the evidence behind it. Present uncertainty and confidence intervals rather than single deterministic labels.
7. Run pragmatic pilots
Before scaling, run real‑world pilots that measure clinical outcomes, user engagement, and unintended effects. Use mixed methods—quantitative metrics and qualitative feedback—to capture nuance.
Practical example: implementing a campus mental health chatbot
A mid‑sized university piloted a chatbot to supplement counseling services. Steps they took:
- Define scope: The chatbot would provide psychoeducation, CBT exercises, and crisis signposting—not therapy.
- Select vendor: Choose a vendor with peer‑reviewed evidence and transparent reporting.
- Consent and privacy: Students opted in; data were anonymized for analytics and encrypted at rest.
- Escalation protocol: The chatbot used validated screening questions and voice markers; high‑risk responses triggered immediate outreach from a human counselor.
- Evaluation: The university tracked symptom scores, help‑seeking behavior, and student satisfaction. They also monitored false positives and adjusted thresholds.
- Iterate: Based on feedback, the chatbot’s language was localized and additional cultural examples were added.
Outcome: increased access during peak demand, faster triage, and high user satisfaction when human follow‑up was available.
Regulatory and policy landscape
By 2026, regulators and professional bodies are increasingly focused on digital mental health. Key trends include:
- Transparency requirements: Expect rules that require disclosure of training data sources, validation studies, and known limitations for clinical tools.
- Auditability: Independent audits and post‑market surveillance are becoming standard for high‑risk applications.
- Human oversight mandates: Some jurisdictions require human clinicians to retain final decision authority in clinical contexts.
- Data protection: Stronger rules on sensitive health data, including explicit consent and limits on secondary use, are emerging.
Organizations should track local regulations and align deployments with professional ethical standards.
Conclusion
Emotional AI offers practical benefits: scalable screening, low‑intensity support, and clinician augmentation. The technology can expand access and help identify people who might otherwise fall through the cracks. Yet it is not a panacea. Evidence is strongest for short‑term, narrowly defined tasks; long‑term outcomes and equity remain open questions. Responsible deployment requires rigorous validation, human oversight, strong privacy protections, and continuous monitoring for bias and harm.
When used thoughtfully, emotional AI can be a valuable partner in mental health care—speeding detection, supporting clinicians, and offering timely help. The imperative for clinicians, product teams, and policymakers is to pair innovation with safeguards so that these tools help people without introducing new risks.
FAQ
1. Are mental health chatbots effective? Some chatbots show small‑to‑moderate short‑term benefits for depressive symptoms, especially when delivering structured CBT exercises. Evidence for anxiety, long‑term outcomes, and real‑world effectiveness is more limited.
2. Can emotional AI replace therapists? No. Emotional AI can augment access and support routine tasks, but it cannot replace the therapeutic relationship, clinical judgment, or complex case management.
3. What privacy protections should users expect? Users should expect explicit informed consent, end‑to‑end encryption, minimal data retention, and clear policies on who can access data. Anonymized aggregate analytics are preferable to identifiable data sharing.
4. How do I know if a tool is fair? Ask for disaggregated performance metrics across demographic groups, independent validation studies, and evidence of bias‑mitigation steps such as diverse training data and fairness testing.
5. What should employers consider before offering emotional AI to staff? Ensure participation is voluntary, data are anonymized for organizational insights, human support is available for flagged cases, and clear boundaries exist between wellbeing programs and performance management.